Overdose or emergency? Call now Hotlines · US 911 · UK 999 · EU 112 · AU 000 · IN 112 · 988 (US crisis) Hotlines
GUIDE · 7 min read

MDMA Nasal Spray: the 'safer' myth, what's actually in it, and the serotonin danger nobody mentions
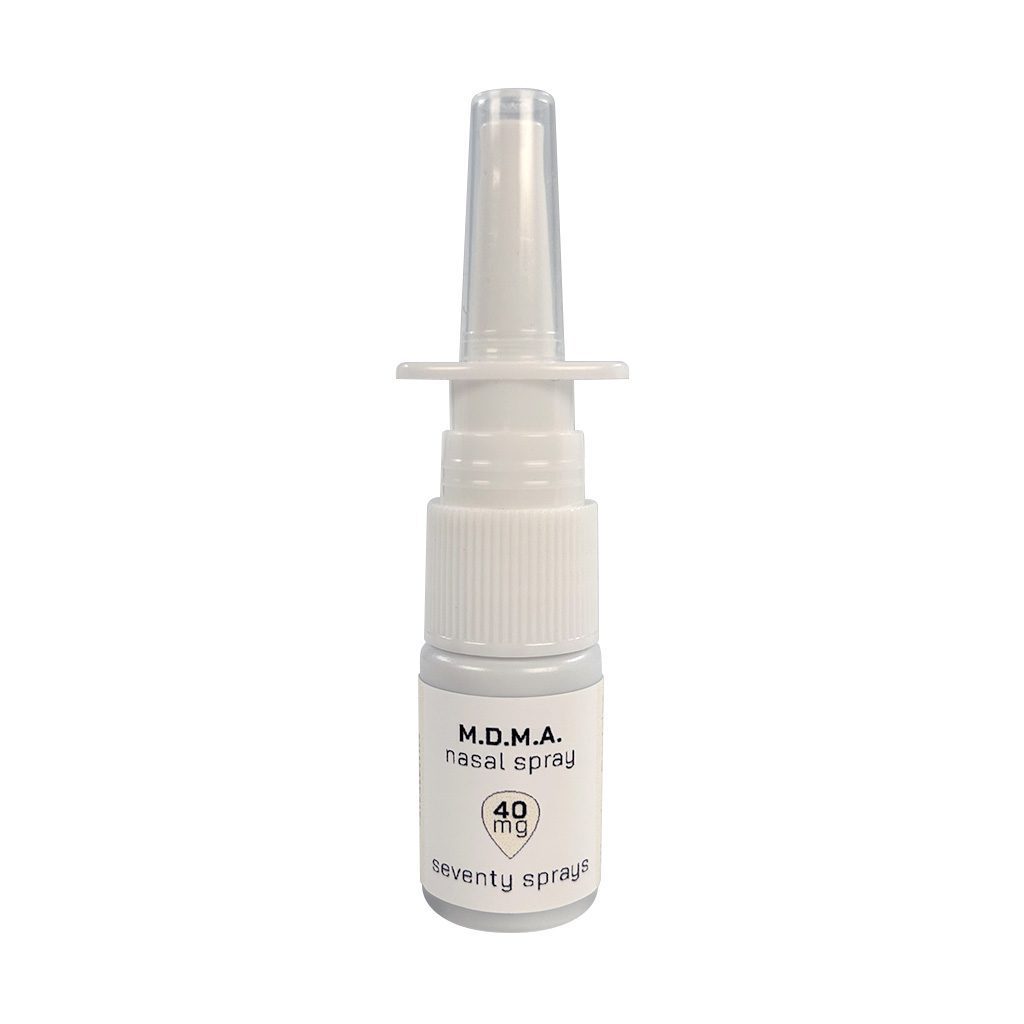
MDMA nasal spray is being marketed on TikTok as a 'cleaner, safer, more precise' way to take ecstasy. The logic sounds appealing: no pill press uncertainty, no waiting an hour, 'just a measured spray.' The reality is almost the opposite: the dose is unknown, the cuts are dissolved in with it, the onset is dangerously fast for a serotonin-heavy drug, and the redose pattern it encourages is the exact mechanism behind MDMA's rare but real deaths.

The core mythSpraying MDMA doesn't make it safer — it makes it faster. And with MDMA, faster is not better. The drug's dangers scale with how hard and how fast it floods serotonin. A spray that hits in 5–10 minutes produces a sharper, more overwhelming come-up, a more brutal comedown, and a far stronger urge to redose. 'Measured' is also a lie when the source is a street powder dissolved in a kitchen bottle.

What is MDMA nasal spray, actually?

There is no pharmaceutical MDMA nasal spray (unlike cocaine, which has a legitimate medical version). What exists online is entirely homemade: MDMA powder or crushed pills dissolved in saline and put into a spray bottle. Some sellers pre-make it; more commonly users DIY it from their own supply. The concentration is anyone's guess — street MDMA is already 30–90% pure, and dissolving it in an unmeasured volume of liquid removes even the rough visual gauge users rely on.

Claim from TikTokReality
'It's measured — one spray, one dose'Spray bottles deliver wildly variable volumes (50–150 mL per squeeze). No street bottle is calibrated. Your 'one spray' could be a quarter-dose or a double.
'No pill presses — pure MDMA'You're dissolving the same powder that was in the pills — including every cut. The spray doesn't purify anything.
'Safer for your nose than snorting'Spraying a caustic, acidic MDMA solution onto the full nasal mucosa is harder on tissue than a line that sits in one spot.
'Hits faster — more fun'Faster onset = sharper serotonin spike = higher core temperature = higher neurotoxicity risk. The 'fun' is the danger.

Why the nasal route changes MDMA's risk profile

MDMA's harms are dose- and rate-dependent. The drug dumps serotonin, norepinephrine, and dopamine; the serotonin surge is what creates the euphoria and empathy — and it's also what drives hyperthermia (overheating), the primary killer in MDMA deaths. When you spray instead of swallow:

  • Onset collapses from 45–60 min (oral) to 5–15 min (nasal) — the body has no time to ramp up temperature regulation
  • The peak is sharper — a wall of serotonin instead of a wave, which is more neurotoxic
  • The comedown hits sooner and harder — the brain's serotonin is depleted faster, the crash is deeper, and the craving to redose is stronger
  • You lose the body's natural brake: swallowing means the drug passes through the stomach and liver first (first-pass metabolism slightly blunts the peak). Nasal spray bypasses that buffer entirely.
The redose trapMDMA's most dangerous pattern is redosing because 'it's wearing off.' When the first spray fades at 60–90 minutes, users spray again — but the drug is still in their system, still dumping serotonin, still raising temperature. Stacked doses are how the rare, fatal cases happen: serotonin syndrome, hyperthermia >40°C (104°F), and multi-organ failure. The rule that saves lives — never redose on a comedown — is precisely the rule nasal spray makes hardest to follow.

What's it cut with? (and why dissolving doesn't help)

Spraying doesn't remove adulterants — it delivers them straight into your bloodstream alongside the MDMA. Current drug-checking data on 'MDMA' powder shows:

What testing findsWhy it matters more in a spray
Caffeine, sugar, inert fillerVariable strength per spray — the 'measured dose' is fiction
Bath-salt cathinones (4-CMC, 3-CMC)Longer, more compulsive stimulation — masks MDMA wearing off, drives redosing
PMA / PMMA (the killer impersonators)Slow onset — users spray more thinking it's weak, then overdose. PMA has killed hundreds of people who thought they took MDMA
Ketamine, speed (amphetamine)Unpredictable stacking of dissociation or extra stimulant load on the heart
Why PMA/PMMA is the nightmare scenarioPMA looks like weak MDMA for 2+ hours — users take (or spray) more, thinking it's bunk. Then it hits: extreme overheating, seizures, and a body temperature that spirals past 42°C (108°F). PMA kills by cooking people from the inside. It has been found in pills and powders sold as MDMA across Europe, Australia, and North America. If a spray or pill takes 2 hours to work, it is NOT more MDMA — it may be PMA. Never redose a slow one.

Serotonin syndrome: the overdose that looks like a 'bad trip'

MDMA overdose is rarely a quiet collapse like opioids. It's a body and mind in catastrophic overdrive — and the most dangerous form is serotonin syndrome, which can look like a panic attack or a bad trip until it's too late:

  • Agitation, confusion, hallucinations — beyond normal MDMA weirdness
  • Rapid heart rate, high blood pressure
  • High fever — >38.5°C (101°F) and climbing is the red flag
  • Muscle rigidity, jerky movements — legs that won't stay still, jaw clenching beyond the normal gurn
  • Sweating, diarrhea
  • Seizures in severe cases
MDMA overdose: what to do1. Call emergency services immediately. Say 'possible drug overdose, high fever, confusion.' Good Samaritan laws protect you. 2. Active cooling is everything — strip layers, fan them, cool damp cloths on neck/groin/armpits. MDMA kills by heat. 3. No more fluids than they can comfortably drink — MDMA can also cause dangerous water intoxication (hyponatremia); sips, not gulps. 4. If they're unconscious but breathing, recovery position. 5. Tell responders it was MDMA — they can treat serotonin syndrome and hyperthermia, but only if they know. Time matters: cooling in the first 30 minutes changes outcomes.

The comedown: why spray users crash hardest

MDMA depletes serotonin. Oral users crash at hour 4–6; nasal users, because the peak came faster, crash at hour 2–4 — and the brain reads the sudden emptiness as an emergency. The Tuesday blues become the 'same-night despair.' Repeated rapid-cycle use (the spray pattern) accelerates the long-term damage: memory problems, depression, anxiety that can persist for months. The brain needs 1–3 months between rolls to rebuild serotonin function — spraying weekly is how people burn out at 22.

If you're going to use anyway (harm reduction)

  • Reagent test the powder FIRST (Marquis/Mecke) — a spray made from PMA is a loaded gun
  • Never redose on a comedown — wait a full 90 minutes minimum, and honestly, don't at all
  • Dose low: a true 75–100 mg oral is the safety ceiling for most people; sprays make it impossible to know
  • Cool down proactively — rest in shade, sip electrolyte water (not more than ~500 mL/hour)
  • Never mix with antidepressants (SSRI/SNRI/MAOI) — serotonin syndrome risk multiplies
  • Never mix with alcohol — dehydration + overheating + impaired judgment
  • Have a sober friend who knows what you took — and have naloxone anyway (contamination happens)
  • If a spray/pill takes 2 hours to work, assume it's PMA — do NOT take more